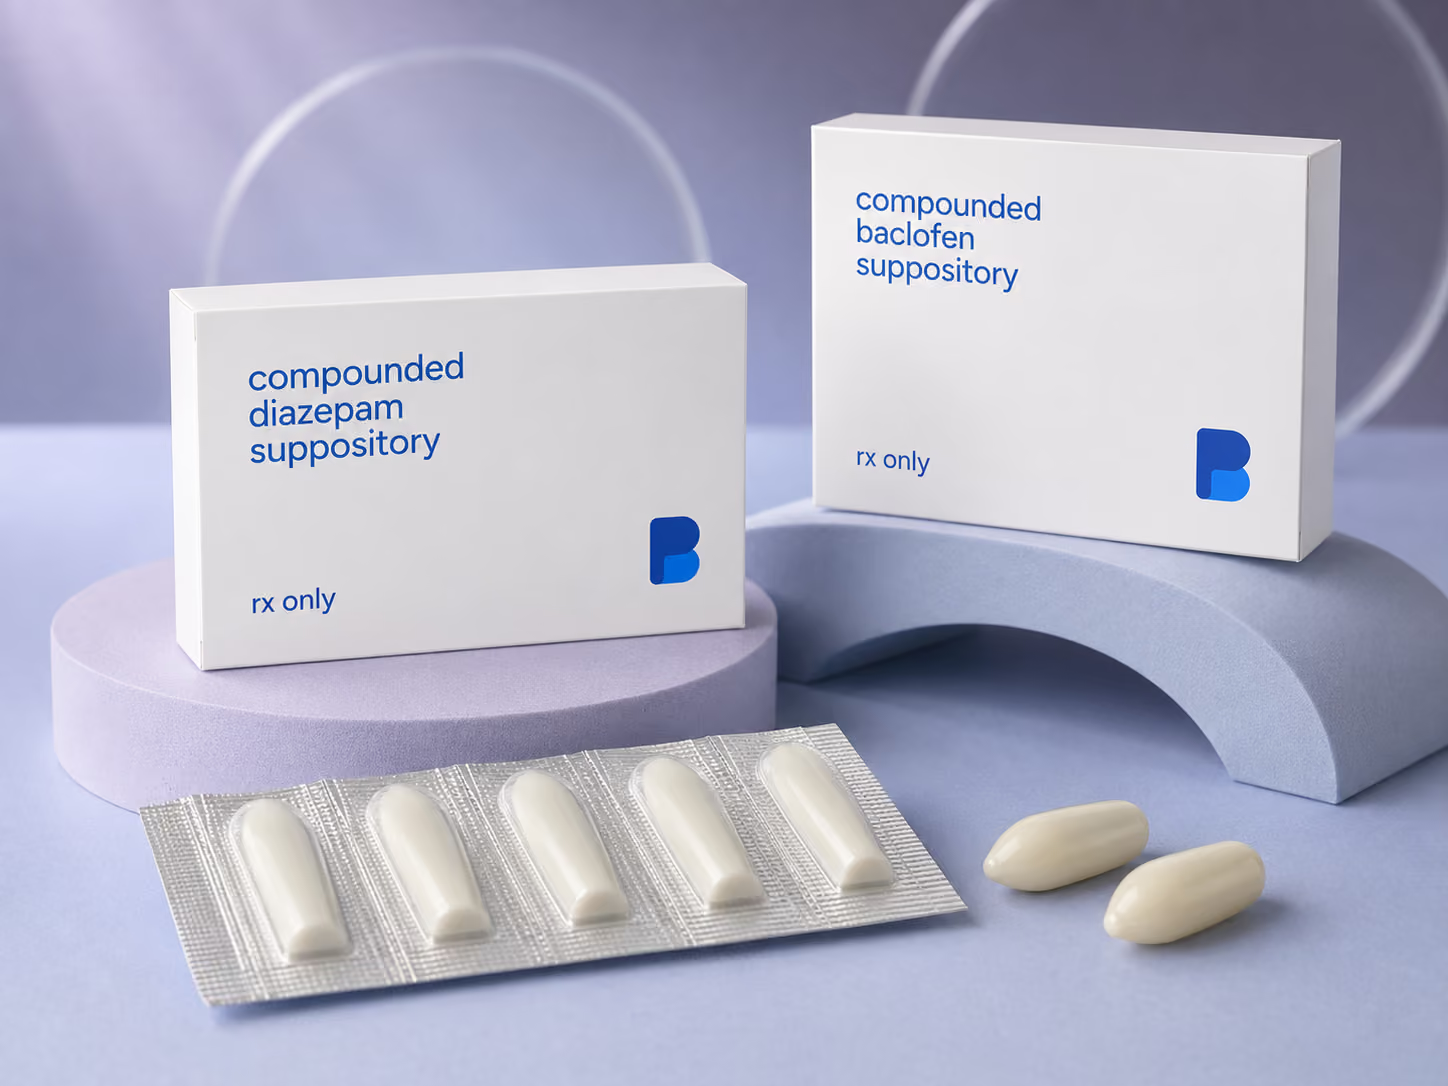





Diazepam and baclofen suppositories are compounded prescription preparations inserted into the vagina or rectum. They can contain diazepam alone, baclofen alone, or both together. The combination prescribed most often is diazepam 5 mg with baclofen 10 mg, and single-agent diazepam 5 mg or 10 mg and baclofen 5 mg to 20 mg suppositories are also made. Some prescriptions add ketamine. Each batch is prepared by a licensed pharmacy to the strengths your prescriber orders.
Diazepam placed in the vagina is often called "vaginal Valium." Valium is the brand name of an FDA-approved oral diazepam tablet. A compounded diazepam suppository is not Valium, and it is not FDA-approved.
Prescribers order these suppositories for hypertonic (high-tone) pelvic floor dysfunction, in which the pelvic floor muscles stay tight and can cause pelvic pain, painful intercourse, or urinary and bowel symptoms. There is no FDA-approved vaginal or rectal suppository of diazepam, baclofen, or any combination of them, so the dosage form itself is unapproved. This page sets out what is actually known, including the findings that do not support it.
How does it work?
Diazepam is a benzodiazepine. It enhances the effect of GABA at GABA-A receptors, which relaxes muscle, reduces anxiety, and causes sedation, largely through the brain and spinal cord. Baclofen is a GABA-B agonist that acts at the spinal cord to reduce muscle spasticity. It is a muscle relaxant, not a benzodiazepine, and it is not a federally controlled substance. Ketamine, when a prescriber includes it, is an NMDA receptor antagonist added with the intent of addressing nerve pain.
The idea behind giving these vaginally or rectally is that the medication sits near the levator ani and obturator internus muscles and may help them relax. That is the reasoning, not a proven effect.
What is it used for?
Prescribers order these suppositories for hypertonic pelvic floor dysfunction and the symptoms that go with it, such as pelvic pain, painful intercourse, vaginismus, and levator ani spasm. They are usually intended as an adjunct to pelvic floor physical therapy, not as a treatment on their own. Prescribers also order diazepam suppositories for other reasons; this page focuses on pelvic floor use.
Benefit is not established for any of these uses, and Bayview makes no claim that these suppositories relieve pelvic pain, vaginismus, or painful intercourse. Only a licensed prescriber can decide whether to try them. Bayview Pharmacy does not provide consultations and does not determine whether a medication is appropriate for you; a valid prescription is required.
What does the evidence show?
Plainly: benefit is not established. The placebo-controlled trials of vaginal diazepam on its own found no difference from placebo.
- Crisp and colleagues, 2013. A triple-blinded trial in 21 women compared nightly 10 mg vaginal diazepam with placebo for 28 nights. There was no difference in resting pelvic floor muscle activity (EMG) at any time point and no difference on any validated questionnaire.
- Holland and colleagues, 2019. A double-blind trial randomized 49 women with levator muscle spasm to 10 mg diazepam or placebo capsules used vaginally, with pain measured at four weeks; 35 had complete four-week data. Pain scores did not differ between the groups (50 mm with diazepam and 39 mm with placebo on a 100 mm scale), and neither did questionnaire scores.
- Murina and colleagues, 2018. In 42 women with vestibulodynia, all of whom also used TENS, pain scores fell in both groups with no significant difference between them. Pain with intercourse and the ability to relax the pelvic floor after a contraction improved more with diazepam than with placebo. This is one small study of diazepam combined with another treatment.
- A 2020 systematic review (Stone and colleagues) found only five studies: two observational studies, in which most women reported improved sexual function without significant changes in pain (VAS) or sexual function (FSFI) scores, and the three small trials above. The authors concluded that more and larger studies are needed.
- Rectal diazepam. The only placebo-controlled trial we found (Aldrich and colleagues, 2022, 130 women randomized, 123 analyzed) gave one 10 mg rectal suppository after vaginal prolapse surgery. It did not reduce pain or opioid use, and the authors did not recommend adding it.
- Baclofen suppositories have no published randomized trial results. A placebo-controlled trial of 20 mg vaginal baclofen at the University of Louisville is listed as completed but had not posted results as of October 2026. The rest of the support is case series and conference abstracts.
- Ketamine has no controlled evidence for this route or this indication.
- No society guideline endorses these. No urogynecology, urology, or gynecology society guideline recommends compounded diazepam or baclofen suppositories as standard therapy.
The honest bottom line is that pelvic floor physical therapy is the intervention with actual evidence for hypertonic pelvic floor dysfunction. If you are considering these suppositories, ask your prescriber how they fit alongside physical therapy rather than in place of it.
Diazepam alone, baclofen alone, or both?
Your prescriber chooses the ingredients. The options Bayview prepares are:
- Diazepam with baclofen. The most common choice, usually diazepam 5 mg with baclofen 10 mg, or 10 mg of each. Schedule IV, because of the diazepam.
- Diazepam alone. 5 mg or 10 mg per suppository, without baclofen. Schedule IV.
- Baclofen alone. Commonly 10 mg, or a custom strength from 5 mg to 20 mg. Baclofen is not a benzodiazepine and is not a controlled substance. It has its own risks, including drowsiness and a serious withdrawal syndrome if stopped suddenly, so it must be tapered.
- Diazepam and baclofen with ketamine. Ketamine is a Schedule III controlled substance, and the FDA has warned about compounded ketamine products (see below).
Vaginal diazepam can also be compounded as a cream or gel on request, which some prescribers order when a suppository does not suit the patient.
How is it used?
Use them exactly as your prescriber directs. As commonly prescribed, one suppository is inserted vaginally or rectally at bedtime, either nightly, every other night, or only on the nights it is needed, and dispensed in a 15-count or 30-count. Because diazepam has a long half-life, the authors of the absorption study suggested intermittent use rather than every night, for example around physical therapy sessions.
Some prescribers set a defined trial, for example a few weeks (the placebo-controlled trials ran about four weeks), rather than open-ended refills. Wash your hands before and after inserting. Because sedation is expected, bedtime dosing is common, and you should not drive or do anything requiring alertness until you know how it affects you, including the next morning. A panty liner can help with leakage from the base. These details describe common regimens and are not treatment recommendations; your prescriber sets the strengths, the schedule, and when to stop.
What strengths are made?
These suppositories are compounded to order. The options below are the ones prescribers request most often.
| Preparation | Route | Count |
|---|---|---|
| Diazepam 5 mg / baclofen 10 mg | Vaginal or rectal | 15 or 30 |
| Diazepam 10 mg / baclofen 10 mg | Vaginal or rectal | 15 or 30 |
| Custom: diazepam 2 to 10 mg / baclofen 5 to 20 mg | Vaginal or rectal | 15 or 30 |
| Diazepam 5 mg or 10 mg (alone) | Vaginal or rectal | 15 or 30 |
| Baclofen 10 mg, or custom 5 to 20 mg (alone) | Vaginal or rectal | 15 or 30 |
| Diazepam / baclofen / ketamine (e.g. 5-5-17.25 mg to 5-5-25 mg) | Vaginal or rectal | 30 |
| Diazepam vaginal cream or gel (e.g. 5 mg/g or 10 mg/g) | Vaginal | As ordered |
Strengths are listed for reference only. None has been shown in a randomized trial to reduce pain more than placebo, and listing them is not a statement that any of them works or that one is better than another.
Side effects & safety
Expect sedation. Drowsiness, fatigue, muscle weakness, and unsteadiness are the side effects reported most often for diazepam. Dizziness, impaired driving and coordination, falls, and problems with memory or concentration can also occur, and all of these are made worse by alcohol and by opioids. Because diazepam stays in the body for days, these effects can last into the next day and can build up with repeated doses. Do not drink alcohol while using these, and tell your prescriber about every medication you take, especially opioids, other sedatives, sleep medications, and muscle relaxants.
Extra caution is needed in older adults (benzodiazepines appear on the Beers criteria list of medications to avoid), and in people with breathing problems, liver impairment, or a history of substance use.
Baclofen can cause drowsiness and muscle weakness. Stopping baclofen abruptly can cause a serious withdrawal syndrome with seizures, fever, confusion, muscle stiffness, and hallucinations, so it should be tapered rather than stopped suddenly, and doses need care in kidney impairment.
Local effects include vaginal irritation, discharge, and leakage or staining from the suppository base. Avoid use in pregnancy and while breastfeeding unless you have had a clear conversation with your prescriber about it.
Who should not use it?
Do not use these if you are allergic to diazepam, baclofen, ketamine (in versions containing it), or any ingredient in the suppository base. Versions containing diazepam are not appropriate if you have a benzodiazepine allergy, acute narrow-angle glaucoma, severe breathing problems (respiratory insufficiency), sleep apnea, severe liver disease, or myasthenia gravis, and they should be avoided or used only with specific direction if you take opioids or have a history of benzodiazepine or other substance misuse. Avoid in pregnancy and lactation absent a clear discussion with your prescriber. Tell your prescriber about your full health history, your allergies, and everything you take, including alcohol and anything bought over the counter.
How should it be stored?
Store them according to your label, because it depends on the base. Polyethylene glycol (PEG) based suppositories are generally kept at controlled room temperature. Cocoa butter and other fatty-base suppositories are generally refrigerated at 2 to 8 °C, or at least kept below 25 °C, so they do not melt. Follow the storage instruction the pharmacy puts on your label.
Protect them from light and heat, and do not store them in a bathroom. Because diazepam is a controlled substance, keep them secured and out of the reach of children and anyone else in the household, and do not share them. Discard after the beyond-use date on the label, and dispose of unused suppositories through a drug take-back program.
Why is this compounded?
There is no FDA-approved vaginal or rectal suppository of diazepam, baclofen, or any combination of them. Diazepam is FDA-approved as oral tablets (Valium and generics), an oral solution, an injection, a rectal gel (Diastat, approved only for acute repetitive seizures), and a nasal spray and buccal film for seizure clusters. Baclofen is approved for oral use and as an intrathecal injection (Lioresal). Ketamine is approved as an injection, and esketamine as a nasal spray (Spravato). A suppository can therefore exist only as a compounded preparation. Some prescribers instead ask patients to insert an oral diazepam tablet vaginally; that is off-label use of an FDA-approved tablet, not a compounded product.
When a prescriber orders a suppository, Bayview Pharmacy prepares it as a 503A compounding pharmacy under USP <795> standards, at the strengths and in the base specified. Compounding makes the dosage form available; it does not make it effective. Compounded preparations are not FDA-approved. Related preparations include Vulvodynia Creams and Medication Tapering. The full list is in our compounded medications catalog.
Clinical details for prescribers
Key evidence. Crisp CC, et al. Int Urogynecol J. 2013;24(11):1915-23 (triple-blinded RCT, N=21; vaginal diazepam 10 mg nightly for 28 nights): no difference in resting vaginal EMG at any time point and no difference on any validated questionnaire versus placebo. Holland MA, et al. Female Pelvic Med Reconstr Surg. 2019;25(1):76-81 (double-blind RCT, N=49 randomized, 35 analyzed; vaginal diazepam 10 mg versus placebo, primary outcome 100-mm VAS at 4 weeks): 50 vs 39 mm, P=0.36, and no questionnaire differences. Murina F, et al. Eur J Obstet Gynecol Reprod Biol. 2018;228:148-53 (double-blind RCT, N=42 with vestibulodynia, all receiving TENS, 60 days): VAS pain reduction did not differ between groups; Marinoff dyspareunia score and post-contraction relaxation on surface EMG favored diazepam. Stone RH, et al. J Clin Pharmacol. 2020;60 Suppl 2:S110-S120 (systematic review, 5 studies): observational reports of subjective improvement without significant FSFI or VAS change; RCTs largely negative. Aldrich ER, et al. Am J Obstet Gynecol. 2022;227(2):302.e1-9 (RCT, N=123 analyzed; single 10 mg rectal suppository after native-tissue prolapse repair): no difference in early postoperative pain or opioid use; the placebo group reported higher satisfaction with in-hospital pain control. Baclofen: no published RCT results; NCT05968937 (University of Louisville; vaginal baclofen 20 mg daily versus placebo, enrollment 39) is listed as completed with no results posted. Ketamine: no controlled evidence for this route or indication.
Bottom line. Benefit is not established. Pelvic floor physical therapy is the intervention with actual evidence for hypertonic pelvic floor dysfunction; suppositories are adjunctive at best. No urogynecology, urology, or gynecology society guideline endorses compounded diazepam or baclofen suppositories as standard therapy.
Pharmacokinetics. Larish AM, et al. J Sex Med. 2019;16(6):763-6 (N=8 healthy volunteers; single 10 mg compounded vaginal suppository): mean Cmax 31.0 ng/mL at a mean Tmax of 3.1 h, bioavailability 70.5%, mean terminal half-life 82 h; nordiazepam peaked at 6.4 ng/mL at 132 h; fatigue in 3 of 8. Vaginal diazepam is not confined locally. Daily dosing accumulates, with steady state not reached for up to a week; the authors suggested the profile favors intermittent use. Counseling that frames the route as "local only" or as having minimal systemic absorption is not accurate.
Regulatory. FDA-approved diazepam products: oral tablets (Valium and generics), oral solution, injection, rectal gel (Diastat, indicated for acute repetitive seizures), and nasal spray and buccal film for seizure clusters. Baclofen: oral products and intrathecal baclofen (Lioresal). Ketamine injection; esketamine nasal spray (Spravato). No FDA-approved vaginal or rectal suppository of diazepam, baclofen, or any combination exists. Diazepam is Schedule IV and ketamine is Schedule III; DEA registration and controlled-substance prescribing, recordkeeping, and refill limits apply. Baclofen alone is not federally controlled. FDA warned on October 10, 2023 about compounded ketamine products, including oral formulations for psychiatric disorders (sedation, dissociation, worsening psychiatric symptoms, blood pressure elevation, respiratory depression, abuse and misuse, lower urinary tract and bladder symptoms), specifically addressing unmonitored at-home use. Compounded preparations are not FDA-approved.
Formulation & SIG. Bayview codes: DB-5-10 (diazepam 5 mg / baclofen 10 mg), DB-10-10, DB-CUST (diazepam 2 to 10 mg / baclofen 5 to 20 mg), DB-D5 and DB-D10 (diazepam alone), DB-K (diazepam 5 mg / baclofen 5 mg / ketamine 17.25 to 25 mg), all vaginal or rectal, 15 or 30 count (DB-K: 30 count). Baclofen alone: DB-B10 (10 mg) and DB-BC (5 to 20 mg). Descriptive SIG: insert one suppository vaginally or rectally at bedtime, nightly, every other night, or as needed, maximum one per day. Prepared under USP <795>.
Clinical points:
- Set a defined trial duration (commonly 2 to 4 weeks) with a stop or taper plan rather than open-ended refills; consider intermittent dosing around pelvic floor physical therapy sessions given the 82-hour half-life.
- Monitor sedation, next-day impairment, cumulative benzodiazepine exposure, and signs of dependence; counsel on driving, alcohol, and concurrent opioids.
- Reassess with pelvic floor examination and validated pain and function measures rather than refill volume.
- Benzodiazepine boxed warnings apply: risks from concomitant opioid use (profound sedation, respiratory depression, coma, death); abuse, misuse, and addiction; dependence and withdrawal reactions, including seizures, on abrupt discontinuation.
- Baclofen requires tapering; abrupt withdrawal can cause seizures, fever, confusion, muscle rigidity, and hallucinations. Reduce dose in renal impairment.
- Diazepam is contraindicated in myasthenia gravis, severe respiratory insufficiency, severe hepatic insufficiency, sleep apnea syndrome, and acute narrow-angle glaucoma. Caution in older adults (Beers criteria), respiratory disease, hepatic impairment, and substance use history. Avoid in pregnancy and lactation absent a clear risk discussion.
- Bayview accepts diazepam- and ketamine-containing prescriptions only as EPCS; baclofen-only suppositories can be faxed on the Baclofen Suppositories order form.
Ordering: e-prescribe to Bayview. Bayview does not recommend this preparation and makes no efficacy claim; it is prepared on prescriber request as an adjunct within a prescriber-directed plan. Sources are listed under Sources reviewed below. Account setup, licensing, and ordering are covered on our for providers page.
This is a prescription compounded medication and is not FDA-approved. This information is educational and is not medical advice, and it is not a recommendation to use this preparation. Benefit for hypertonic pelvic floor dysfunction, pelvic pain, vaginismus, and painful intercourse is not established; placebo-controlled trials of vaginal diazepam on its own found no difference from placebo, and pelvic floor physical therapy is the intervention with actual evidence. Diazepam is a Schedule IV controlled substance. Your prescriber determines whether it is appropriate and sets the strengths and directions. A valid prescription is required.